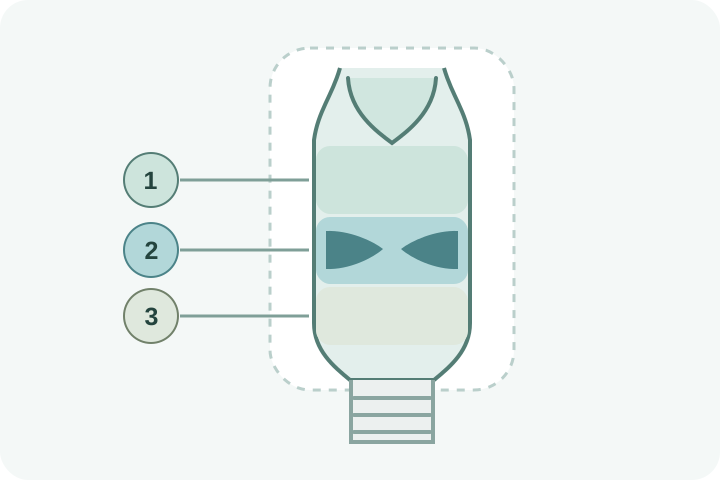
Numbered locations, not stages or a map for diagnosing oneself. Conceptual anatomy, not to scale; the pharynx is not depicted.
- 1 · Supraglottis
Above the vocal cords; includes the epiglottis.
- 2 · Glottis
The region containing the vocal cords.
- 3 · Subglottis
Below the vocal cords, towards the trachea.
Three locations within the voice box—not three stages
The pharynx is the passage behind the nose and mouth; its oropharyngeal part includes the tonsils and tongue base. The larynx is a different structure, containing the vocal cords. ‘Throat cancer’ is too broad to tell you which is affected.
Within the larynx, the supraglottis lies above the vocal cords and includes the epiglottis; the glottis contains the vocal cords; the subglottis lies below them, towards the trachea. These names locate an origin. They are not early, middle and late cancer, and most laryngeal cancers are squamous-cell cancers of the lining rather than cancers of the cords' muscle.
Tobacco and alcohol are not alternative explanations
Both belong to the laryngeal-cancer risk picture. Their combined exposure matters rather than one cancelling the other. Population evidence about a combination is not a calculator in which cigarette and drink counts establish a person's probability or a safe allowance.
Stopping smoking removes ongoing tobacco exposure and reduces cancer risk over time in populations. It does not prove that an existing lesion is benign, clear a diagnosed tumour or restore the voice. The absence of one exposure does not rule out cancer or make the other irrelevant.
An HPV-related ‘throat cancer’ headline still needs a location
Consider an invented headline used only to explain terminology: ‘HPV-linked throat cancer’. If it concerns a tonsil or tongue-base cancer, it concerns the oropharynx, not automatically the larynx. These neighbouring areas can share the label squamous-cell carcinoma while differing in the evidence about what caused the disease.
Finding viral material and establishing a causal role are also different questions. The HPV pattern established for oropharyngeal cancer is not a reason to label a laryngeal cancer HPV-caused, dismiss tobacco or infer an individual's sexual history. Site and clinical findings matter more than an umbrella word.
A voice change describes a function, not the cells
Hoarseness can occur with laryngeal cancer and with other conditions. Hearing a change does not identify a cell type, locate a tumour or determine its stage; a normal-sounding voice does not establish that every part of the larynx is normal. This is why a symptom and an anatomical or tissue finding are not interchangeable.
For personal concerns in England, the NHS directs people to a GP. An established laryngeal condition remains with its responsible team. A useful starting question is ‘Are we discussing the larynx, the pharynx, or a voice-function problem—and what has actually been established?’ Tobacco support can accompany that work without replacing it.
What to keep in mind
Sources
The central claims on this page were checked against the sources below.
- U.S. National Cancer Institute: Laryngeal cancer: supraglottis, glottis, subglottis and squamous-cell origin
Sources checked: 2026-10-10
- U.S. National Cancer Institute: Larynx versus pharynx; tobacco, alcohol and HPV site specificity; May 2021
Sources checked: 2026-10-10
- U.S. National Cancer Institute: Tobacco and alcohol exposures, combined risk and cessation; November 2024
Sources checked: 2026-10-10
- NHS: England NHS: laryngeal risk backgrounds and GP assessment; September 2025
Sources checked: 2026-10-10
Population education without individual cause attribution, symptom triage, voice self-testing, screening or treatment selection. No promise of voice recovery or cancer clearance after quitting.